










Pseudo Gynecomastia
This guide explains Pseudo Gynecomastia, including its causes, symptoms, differences from true gynecomastia, diagnosis, weight-loss response, liposuction, skin excess, and treatment options.

- Last updated
- 80 reads
- 8 min read
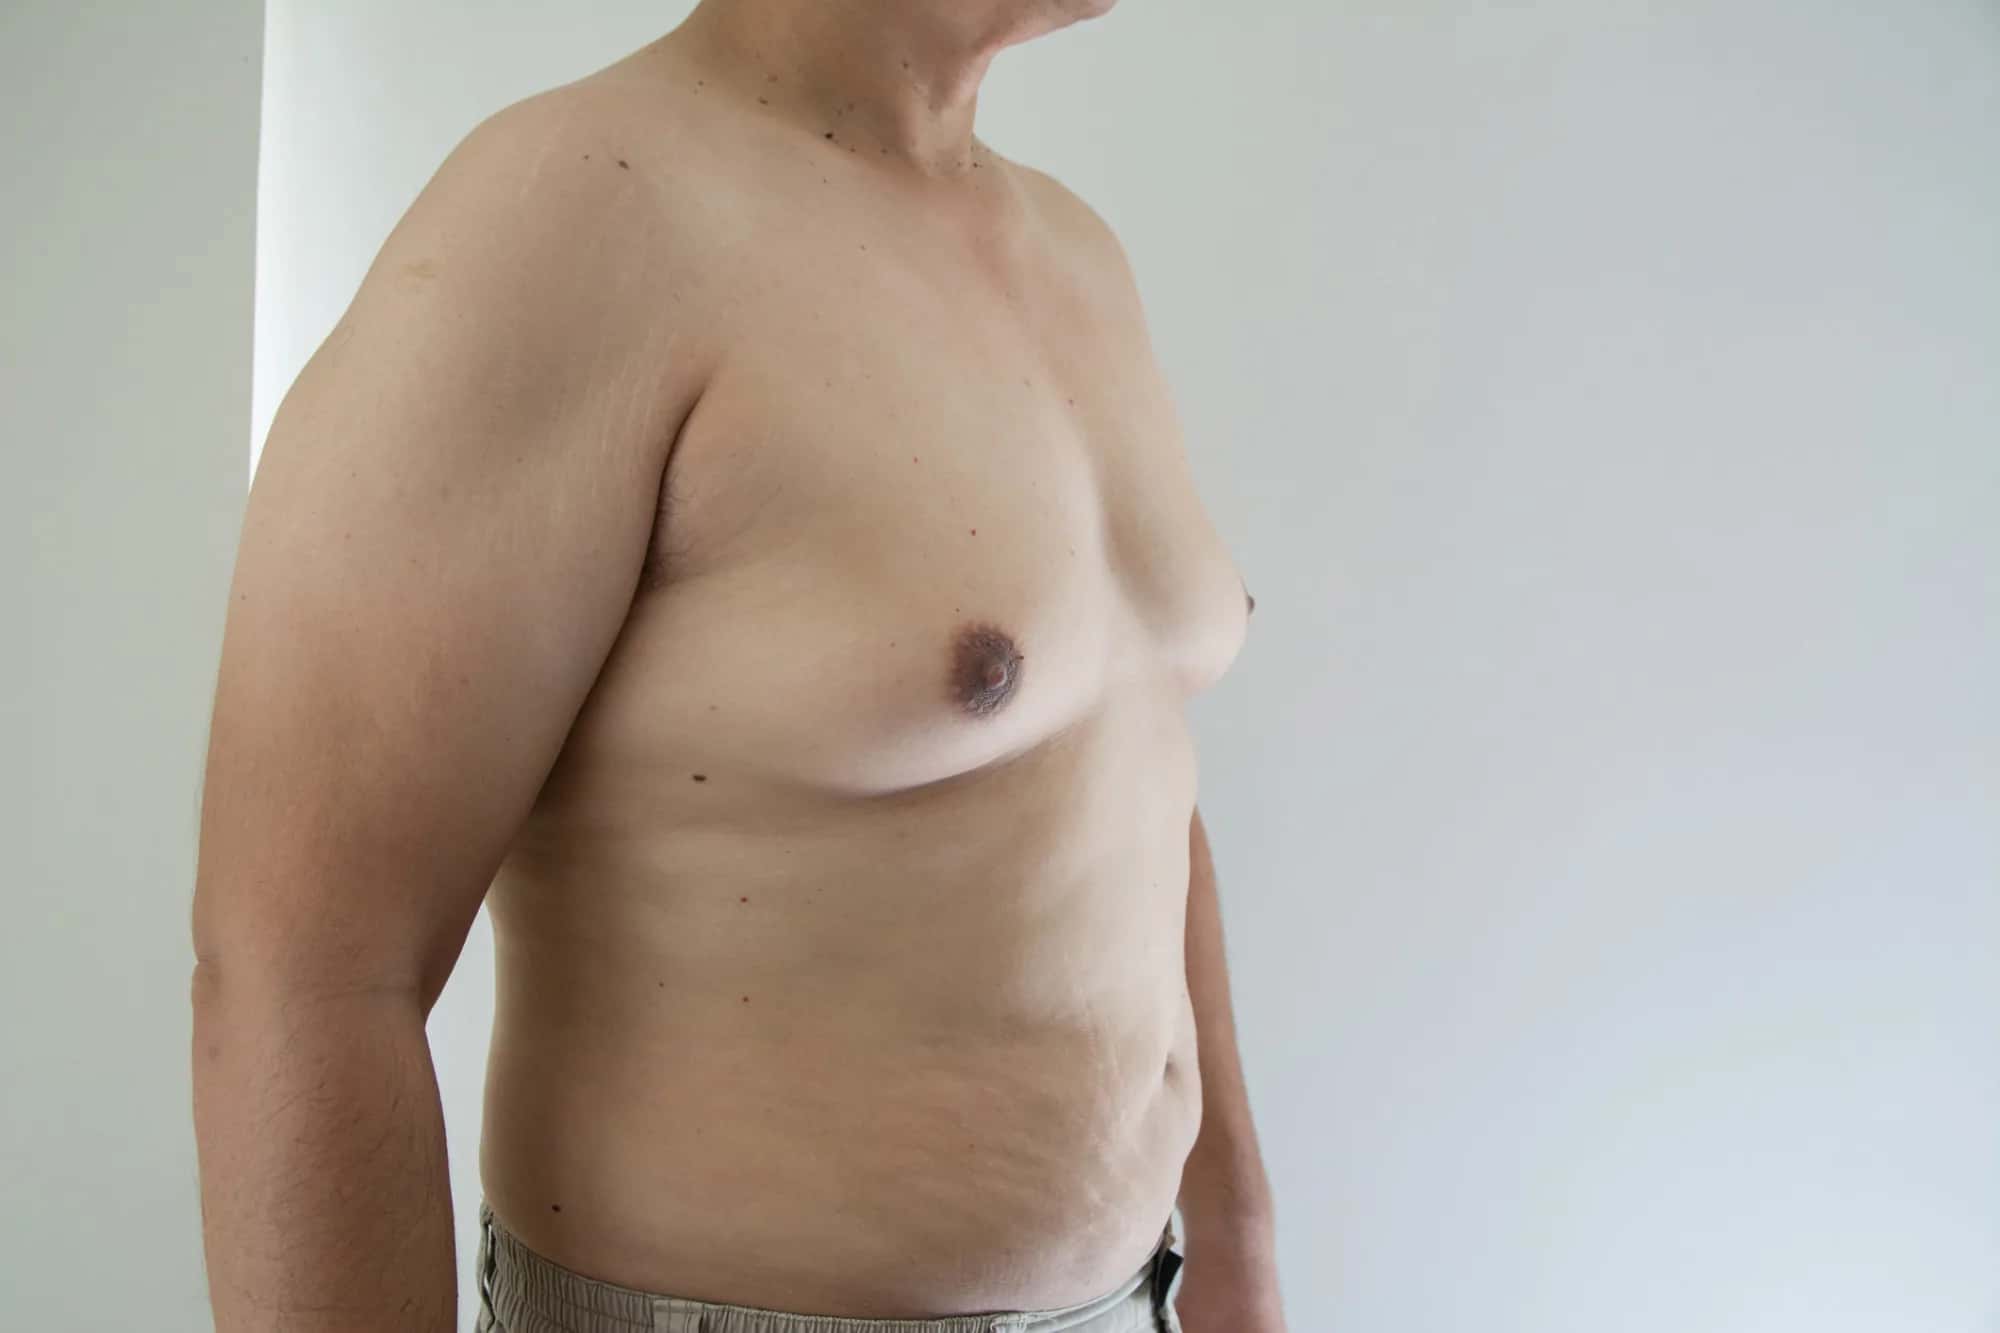


What Is Pseudo Gynecomastia?
Pseudo Gynecomastia is male breast enlargement caused primarily by excess fatty tissue without abnormal proliferation of the underlying breast gland.
The medical term is also written as pseudogynecomastia, while adipomastia and lipomastia are commonly used for the same presentation. The enlarged chest usually feels soft and diffuse rather than forming a firm disc beneath the nipple. It often appears on both sides and can accompany increased body fat. However, it is not limited to men with obesity. The distinction from true gynecomastia matters because fatty and glandular chest enlargement respond differently to weight loss and surgical treatment.
What Causes Pseudo Gynecomastia?
Pseudo Gynecomastia develops when excess adipose tissue accumulates across the male breast without a corresponding increase in glandular breast tissue.
Overall weight gain is a common contributor because increasing body fat can enlarge the subcutaneous fatty layer across the chest. Individual fat distribution also matters, which explains why some men carry proportionally more fat around the breasts. Pseudogynecomastia can therefore occur without severe obesity. The condition differs from hormonally driven gynecomastia because the primary tissue involved is ordinary adipose tissue. Significant weight changes can also alter its appearance over time, particularly when skin elasticity decreases.
What Are the Symptoms of Pseudo Gynecomastia?
Pseudo Gynecomastia usually appears as soft, diffuse male breast enlargement without the firm subareolar tissue characteristic of true gynecomastia.
Typical features include:
-
Soft fatty fullness across one or both breasts
-
Diffuse rather than nodular enlargement
-
Enlargement that blends into surrounding chest fat
-
Greater chest volume after overall weight gain
-
Reduced fullness when body fat decreases
-
Absence of a distinct firm gland beneath the nipple
-
Possible loose skin after major weight loss
-
Usually bilateral or relatively symmetrical enlargement
Pain, nipple discharge, skin retraction, or a hard fixed lump are not typical features of uncomplicated pseudogynecomastia.
What Does Pseudo Gynecomastia Feel Like?
Pseudo Gynecomastia usually feels soft and compressible because the enlarged male breast consists predominantly of adipose tissue rather than dense glandular tissue.
The fatty layer often blends gradually with the surrounding chest and does not create a clearly defined central mass. True gynecomastia commonly feels different during palpation. It can produce a rubbery or firm disc positioned concentrically beneath the nipple and areola. Mixed cases complicate self-examination because soft fat can surround a smaller glandular component. Clinical palpation is therefore more useful when treatment decisions depend on determining whether fat, gland, or both contribute to the chest enlargement.
What Is the Difference Between Pseudo Gynecomastia and Gynecomastia?
Pseudo Gynecomastia is caused by excess breast fat, while true gynecomastia involves benign proliferation of glandular tissue beneath the nipple.
True gynecomastia commonly produces a firm or rubbery subareolar disc that can feel distinct from surrounding fat. Pseudogynecomastia lacks this glandular enlargement and usually feels softer throughout the chest. Their causes also differ. Gynecomastia can reflect hormonal changes, medications, systemic illness, or physiological changes during puberty and ageing. Pseudogynecomastia is primarily related to adipose tissue accumulation. Because both conditions can occur together, an enlarged male chest cannot always be classified accurately from appearance alone.
Is Pseudo Gynecomastia Related to Obesity?
Pseudo Gynecomastia is frequently associated with overweight and obesity, but excess body weight is not required for the condition to develop.
Increasing total body fat often increases fatty tissue across the chest, making pseudogynecomastia more noticeable. However, research describing the condition specifically notes that it is not necessarily associated with constitutional obesity. Genetics and individual fat distribution can leave some men with disproportionate chest fullness despite a more moderate body weight. Obesity can also coexist with true gynecomastia. In that situation, the chest may contain a combination of enlarged fat and glandular tissue rather than pure pseudogynecomastia.
Can Weight Loss Reduce Pseudo Gynecomastia?
Weight loss can reduce Pseudo Gynecomastia because the enlarged chest primarily consists of adipose tissue that can shrink as total body fat decreases.
The amount of improvement varies because fat distribution and skin elasticity differ between individuals. Some men notice substantial chest reduction during weight loss, while others retain localized fullness after losing fat elsewhere. Major weight reduction can create another issue because stretched skin may remain after the underlying fatty volume decreases. A persistent firm structure beneath the nipple after substantial weight loss can also indicate coexisting true gynecomastia. Weight reduction therefore helps address the fatty component but does not correct every possible cause of male chest enlargement.
Can Exercise Get Rid of Pseudo Gynecomastia?
Exercise can help reduce Pseudo Gynecomastia by supporting overall fat loss and improving chest shape, although the amount of localized fat reduction remains individually variable.
Resistance training strengthens the pectoral muscles underneath the fatty layer, which can improve overall chest proportions. Aerobic and resistance exercise can also reduce total and regional body fat when sustained over time. Research into targeted fat reduction remains mixed, so chest exercises should not be treated as a guaranteed method for selectively removing breast fat. A structured weight-management program is more relevant when pseudogynecomastia accompanies excess total body fat. Persistent localized fat can remain despite improved fitness.
Can Pseudo Gynecomastia Cause Puffy Nipples?
Pseudo Gynecomastia can contribute to puffy-looking nipples when surrounding breast fat pushes the nipple and areola forward, but this appearance does not identify the tissue type reliably.
True gynecomastia can create similar projection because glandular tissue commonly grows directly beneath the nipple. Mixed fatty and glandular enlargement can make the distinction even less obvious. Nipple appearance therefore provides less diagnostic information than palpation of the tissue beneath it. A soft, diffuse chest supports pseudogynecomastia, whereas a firm central disc is more typical of glandular enlargement. Persistent nipple projection after significant fat loss may justify assessment for a residual glandular component.
Can Pseudo Gynecomastia and True Gynecomastia Occur Together?
Pseudo Gynecomastia and true gynecomastia can occur together, producing an enlarged chest containing both excess fat and proliferated glandular tissue.
This mixed presentation is especially relevant in men who carry excess body fat but also have a palpable gland beneath the nipple. Weight loss can reduce the fatty component while leaving glandular projection increasingly visible. Surgical treatment can also require two approaches. Liposuction removes excess adipose tissue, while dense glandular tissue may need direct excision. Treating only the fat can leave residual nipple projection when an important glandular component remains. The tissue composition therefore matters more than overall chest size when planning correction.
How Is Pseudo Gynecomastia Diagnosed?
Pseudo Gynecomastia is usually diagnosed through physical examination showing diffuse soft breast fat without a firm glandular disc centered beneath the nipple.
Assessment commonly begins with inspection of chest shape, symmetry, nipple position, skin quality, and surrounding body fat. Palpation then helps distinguish soft adipose tissue from a denser subareolar gland. The clinical history also matters when enlargement developed suddenly or accompanies medication changes or systemic symptoms. Typical pseudogynecomastia does not automatically require extensive laboratory or hormonal testing. Additional investigation becomes more relevant when the examination suggests true gynecomastia, an unusual mass, or another underlying breast disorder.
Is Ultrasound Needed for Pseudo Gynecomastia?
Ultrasound is usually unnecessary when examination clearly shows uncomplicated Pseudo Gynecomastia, but imaging can help when the breast findings remain uncertain or atypical.
On ultrasound, pseudogynecomastia appears predominantly as lobules of normal adipose tissue without significant enlargement of breast parenchyma. Current imaging guidance does not routinely recommend imaging when clinical findings are clearly consistent with gynecomastia or pseudogynecomastia. Imaging becomes appropriate when there is an indeterminate or suspicious mass. In younger men, ultrasound can be used first for an uncertain lump. Older men with suspicious findings may require mammography or digital breast tomosynthesis as part of the assessment.
Can Pseudo Gynecomastia Remain After Major Weight Loss?
Pseudo Gynecomastia can remain after major weight loss when residual chest fat combines with stretched skin, tissue descent, and changes in nipple position.
Post-weight-loss cases can differ considerably from ordinary fatty chest enlargement. The patient may have lost most excess adipose volume but remain with redundant skin extending across the front and sides of the chest. The nipple-areola complex may also sit lower than normal. Recent surgical research describes this pattern without enlargement of the glandular component. Treatment can therefore require chest lifting or skin excision rather than further fat removal alone. Stable body weight is especially important before planning correction for these post-weight-loss changes.
How Is Pseudo Gynecomastia Treated?
Pseudo Gynecomastia is treated by reducing excess chest fat, with weight management or liposuction used according to body composition and the persistence of localized enlargement.
Weight reduction is the logical initial approach when pseudogynecomastia accompanies increased overall body fat. Persistent fatty fullness can be treated surgically when weight is stable and the chest remains disproportionately enlarged. Liposuction is particularly suited to fat-dominant cases with adequate skin elasticity. Major skin redundancy requires a different approach because reducing volume alone cannot remove hanging skin. Surgery after massive weight loss may therefore combine tissue excision, chest reshaping, and repositioning of the nipple-areola complex.
Does Liposuction Work for Pseudo Gynecomastia?
Liposuction can effectively reduce Pseudo Gynecomastia when excess fatty tissue is the main cause of enlargement and the overlying skin can contract adequately.
The technique removes subcutaneous chest fat through small access incisions and can create a flatter transition over the pectoral region. Its limitations become important when firm glandular tissue is also present. Liposuction may reduce surrounding fat while leaving the gland beneath the nipple unchanged. Significant loose skin can also remain after fat removal, particularly following major weight loss. Surgical reviews therefore support tailoring treatment to the actual tissue composition instead of applying one technique to every enlarged male chest.
Can Pseudo Gynecomastia Come Back After Treatment?
Pseudo Gynecomastia can become noticeable again after treatment if substantial weight gain enlarges the remaining fat cells within the chest.
Liposuction removes selected adipose cells, but it does not prevent future weight gain or eliminate every fat cell from the treated area. Maintaining a relatively stable weight therefore helps preserve chest contour after surgery. Ageing can also change skin elasticity and alter the appearance over time. Recurring projection directly beneath the nipple should not automatically be considered recurrent chest fat because a previously unnoticed glandular component may remain. Stable long-term results depend on matching the original treatment to fat volume, skin quality, and any coexisting gynecomastia.
When Should Male Chest Enlargement Be Medically Assessed?
Male chest enlargement should be medically assessed when it includes a new hard lump, marked one-sided change, nipple discharge, skin retraction, or another unusual breast finding.
A firm fixed mass deserves particular attention, especially when it is not centered beneath the nipple. Nipple inversion, bloody discharge, skin dimpling, redness, scaling, or enlarged lymph nodes also require evaluation. These findings do not automatically indicate a malignant condition, but they are not typical of uncomplicated pseudogynecomastia. Imaging can then be selected according to age and examination findings. A straightforward soft fatty enlargement without suspicious features generally follows a different diagnostic pathway from an unexplained breast mass.
- Last updated
- Language
- English
How did you find this article?
Liposuction has become part of a more open conversation about cosmetic surgery, with celebrities discussing everything from subtle body contouring to difficult recoveries and results they later regretted. These 20 public figures have personally acknowledged undergoing liposuction, offering different perspectives.

Many actors, models, musicians and television personalities have spoken openly about having rhinoplasty, some for cosmetic reasons and others to repair an injury or improve their breathing. This guide looks at what 20 of these celebrities said about their own nose surgery and what their experiences can teach anyone.
Several well-known musicians, reality stars and influencers have spoken openly about having a Brazilian butt lift, and many of them have also shared regret, reduction surgery or difficult recoveries. This guide looks at what these celebrities said about their own procedures and what their experiences can teach anyone.
Subscribe to the Medifinder newsletter and never miss our latest content.